Bone plays an important role as a structure that supports the body and stores calcium. It retains fracture resistance by remodelling through a balance of bone resorption and formation. Bones are usually dense and strong enough to support your weight and absorb most kinds of impact. As you age, bones naturally lose some of their density and their ability to regrow/remodel themselves.  Bone Remodelling Cycle. Source: Author In a microgravity environment, because of reduced loading stimuli, there is increased bone resorption and no change in or possibly decreased bone formation, leading to bone mass loss at a rate of about ten times that of osteoporosis. Life in the microgravity environment of space brings many changes. Loss of bone mass is particularly noticeable because it affects an astronaut’s ability to move and walk upon return to Earth’s gravity. Human spaceflight was once a fantasy only to be found in between the pages of a novel or on movie screens, however, now it is almost a tangible reality. Humans are going to spend more time in space. The human body is intrinsically adapted to Earth’s gravity, so exposure to conditions of reduced gravity, or microgravity can cause complications in many normal bodily functions. Microgravity decreases the effort required for movement.The length of space missions—and consequently the amount of time astronauts spend in orbit—has increased since humans began exploring space. Space travellers are exposed to numerous stressors while in space. The reduced mechanical loading of weight-bearing bones caused by microgravity (μg) leads to bone loss in humans, especially in long-term space missions. As previously mentioned, this bone loss results from increased bone resorption and either unchanged or decreased bone formation, as observed in various human studies conducted both in space and during bed rest. Microgravity causes calcium to be released from bones, which suppresses parathyroid hormone (PTH) and lowers circulating levels of 1,25-dihydroxyvitamin D, although concentrations of 25-dihydroxyvitamin D remain adequate. This process reduces calcium absorption in the body.  Source: InnovaSpace The decrease in bone formation is associated with impaired osteoblast function and increased osteocyte apoptosis. Physical exercise using devices such as treadmills and resistive exercise equipment can help reduce the negative impact of microgravity on bones and muscles. Weight training and aerobic exercise are designed to simulate the mechanical loads normally exerted by gravity on Earth.
Proper nutrition and the use of supplements—such as vitamin D and calcium—are important to support bone health during and after a space mission. Rehabilitation programs include structured physical exercise, physical therapy, and nutritional monitoring to ensure optimal recovery. Together, these countermeasures aim to preserve musculoskeletal health in space and promote a successful transition back to Earth's gravity. Continued research is essential to refine these strategies for longer missions, such as those to the Moon or Mars.
The webinar, organised by InnovaSpace Director Prof Thais Russomano, was presented by 4 students from the Remote Medicine iBSc program, National Heart & Lung Institute, Imperial College London, and in association with the MVA (Moon Village Association). The focus of the event was on one of the most critical aspects of future lunar habitation: human health. Join the student panel as they explore the unique environment of the Moon, the history of its human exploration from NASA Apollo Mission first steps to future Artemis plans, its potential impact on human physical health and mental well-being, Moon research and Earth-based space analogues, and research limitations and gaps in the knowledge. Congratulations to the presenters - Manvi Bhatt, Nareh Ghazarians, Diya Raj Yajaman, & Elvyn Vijayanathan - and good luck with your future careers. With our very own Prof Thais Russomano having recently contributed to the published article - "Space Nursing for the Future Management of Astronaut Health in other Planets: A Literature Review", we thought we would highlight this niche area of nursing and ask good friend Lisa Evetts to write a few words about the role she undertook in 2011 as a Flight Nurse at the European Astronaut Centre in Cologne, Germany. Many thanks to Lisa for agreeing to give us an insight into the work with which she was involved.
I became involved in Space research whilst my husband was completing his PhD in the early 90s, acting as ‘flight nurse’ for several parabolic flight human research studies. I went on to co-develop the Evetts/Russomano (ER) technique for basic life support in space, while continuing to work as a renal specialist nurse in the UK.  Performing CPR using Evetts-Russomano technique, ESA parabolic flight campaign 2000 In 2011, I became the sole flight nurse for the European Astronaut Centre in Cologne, Germany. I enjoyed two successful years working closely with the flight surgeons within the Operational Space Medicine Unit (OSMU), as it was called then. I was part of a team responsible for the day-to-day management and administration necessary for maintaining ESA (European Space Agency) Astronaut health. One of my key responsibilities was to track and retrieve data from medical events related to ‘pre’, ‘in’ and ‘post’ space flight activities. The role also involved working as the interface between OSMU, NASA, the ESA flight clinic and occasionally the Russian Space Agency, coordinating somewhat complex planning to ensure all flight medical examinations were completed within a rigid timescale from an Astronaut’s initial mission assignment, 18 months before they flew, to two years post-mission. The examinations took place at the locations of all 3 agencies to accommodate an Astronauts packed international training schedule. Astronauts who weren’t assigned to a mission, also required coordination of annual medicals locally.  European Astronaut Centre, Cologne (Photos: ©ESA) I particularly enjoyed good relationships with the NASA flight nurses who I had the pleasure to meet when visiting the Johnson Space Center in Houston. It was a great opportunity to meet all those I had been communicating with by phone and email, to cement our good working relationships. I represented OSMU at weekly events such as the astronaut training coordination meetings, where planning and updates on training schedules and upcoming flight assignments would be discussed. Each team involved in preparing an Astronaut for flight was granted a certain number of hours of the astronaut’s time from a packed pre-mission schedule, to complete the necessary training and preparatory requirements. Arduous negotiations were required with other departments and the agency central mission organisation authority, should a team think they needed extra time to complete their activities. As the Flight Nurse I was responsible to lead weekly clinical meetings to update the flight surgeons on any new information and issues relating to an astronaut’s health and the work underpinning their welfare.  Nurses have been associated with the space program from the very beginning of human spaceflight, with Dee O'Hara being appointed in November 1959 as the first nurse of the NASA Mercury Program. Although a niche area, more opportunities for space nurses are emerging with the involvement of commercial entities such as SpaceX and will continue to grow with the arrival of space tourism and plans to return to the Moon.
Author: Dr. Paul ZilbermanMedical Doctor, Anaesthetist, Hadassah Medical Center Jerusalem, Israel
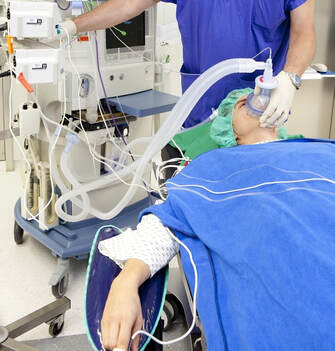
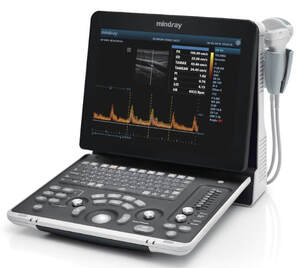
Space is very different, in many aspects. This post does not attempt to address the many changes the human body experiences in space, such as volume modifications in body compartments, fluid shifts, structural configuration in receptor* morphology and, as a consequence, possible variations in pharmacology response, etc. * For the lay reader, a receptor is a special structure on the surface of a cell, for example, that functions as a "receiving point" on which a chemical substance acts in a unique way (like a key – lock mechanism) and a specific reaction is generated (like a muscle contraction) or inhibited (like a cork closing a bottle and blocking the passage of a fluid). These complex structural changes modify many biological reactions, as well as the body’s response to medications. Rather, this post presents some of the technical challenges that an anaesthesiologist may encounter in space. Confined space. On Earth gravity keeps everyone’s feet on the ground. Different pieces of equipment can be repositioned depending on the procedure, machinery can be brought in as needed (XRay scans in orthopaedics, for instance), electric cables can be switched to other convenient wall sockets etc. In a fixed volume space capsule, you don’t have all these possibilities. Everything is measured for maximum volume efficiency. Taking into consideration that anything can and will float if not properly anchored, we can imagine what an “anaesthesia dance” could happen! What equipment? On Earth an anaesthesia workstation is always present in the OR. Depending on its complexity its volume can vary between a medium size fridge to a large double-doored one, just put on its side. You don’t have this amount of deposit in a space cabin, but let’s suppose for one moment that you do - you then need an Anaesthesia Gas Scavenging System (AGSS), which removes the anaesthesia gases that have leaked out or at the end of the procedure. On Earth, these gases are expelled into the atmosphere (there is a lot to talk about this and the greenhouse effects too) and the air currents around any medical facility carry them away. In space you don’t have this. Any gas must be expelled using energy, an active process. Otherwise, the whole cabin will become a big anaesthesia machine with all crew members affected. And, speaking of energy, an anaesthesia workstation is also powered by electricity, which is a limited resource in space, depending on the surface of the solar (or light in general) panels. This energy must be stored and used for other life maintenance systems as well, of which a critical example is the Sabatier reactor that provides oxygen. Regional anaesthesia The simplicity and portability of the necessary equipment makes this type of anesthesia attractive. For peripheral neural blocks all you need is a simple ultrasound machine and dedicated needles. The potential drawbacks are that the technique/s need to be taught on Earth but their “transposition” to space is a bit problematic. If the spinal/epidural anaesthesia is relatively simple to learn, the USG (ultrasound guided) blocks are more challenging. Furthermore, the bodily fluid shift due to the lack of gravity causes many tissues to change their tridimensional appearance, leading to increased difficulty in performing the block.
The cardiovascular responses that accompany spinal/epidural anaesthesia on Earth, in terms of heart rate and blood pressure, are different in space. There may be a lack of reactivity so a certain reduction in blood pressure, for example, might not be compensated. We need to remember that the hostile environment in space, especially radiation, affects not only the human body, but also many sensitive electronic components of medical equipment, leading to possible dysfunction. Monitors can potentially de-calibrate and all the information you receive may become inaccurate. Fluids Preparing and administering a fluid on Earth is routine, however, the lack of gravitation in space poses other challenges: air and fluids do not mix. It is called “lack of buoyancy”. Unless we use special equipment to separate fluids from air nothing can be delivered to the patient. This statement is true also for the anaesthesia vaporiser (a special closed recipient that contains the anaesthesia substance); not only can you not simply fill it the way it would be done on Earth, but even if you could, the anaesthesia liquid that becomes vapour cannot separate from the fluid from which it originates. It just cannot exit the vaporiser. Below is a small example of how liquids behave in space and what happens when a liquid exits a recipient: The same is true for another type of anaesthesia, called TIVA = Total Intra Venous Anaesthesia. This technique uses a dedicated syringe pump that pushes different anaesthesia substances through an intra venous line. It’s a useful technique both in terms of volume and energy expenditure, but again we face the same problems: how to fill the syringe without air bubbles and how to protect the electronics of the syringe pump (in fact a computer in all respects) from the deleterious influences of space radiation!
As you can see, space medicine is a very important topic and many people dream of its future use. Yet, we still have a long way to go! With the advent of intermediary space “stops” and the continuous development of new technologies, every challenge will be solved, sooner or later. Author: Prof K GanapathyDirector Apollo Telemedicine Networking Foundation, Apollo Tele Health Services | Distinguished Visiting Professor IIT Kanpur | Distinguished Professor The Tamilnadu Dr MGR Medical University | Emeritus Professor National Academy of Medical Sciences  5G is the fifth generation of wireless communication technology, promising faster data transfer speeds, lower latency (round trip latency >10 milliseconds), increased network capacity (1 million devices per sq km), 99.999% network reliability and battery life of up to 10 years for IoT devices. There is considerable hype in the media that deployment of 5G will revolutionize healthcare by enabling new medical applications and improving existing ones. Using Edge computing, 5G Data can be processed closer to where it is generated. IoMT (Internet of Medical Things) devices generate huge amounts of data. Cloud computing can provide the necessary infrastructure to process and analyze this data. Faster transmission of data will enable more efficient storage in the cloud. Accessing more bandwidth and computing resources, and providing infrastructure to enable scalability will now be less problematic. No doubt clarity of images transmitted will be better and the immersive experience in video conferencing will be an all-time high. Mammograms, CT, MRI, and ultrasound images generate large amounts of data. High-speed transfer and processing will save a few minutes. Onboard cameras, camera-based Headgear, and ‘Body Cams’ for paramedics can transmit patient data to hospitals in real-time using ultra-fast and low-latency 5G connected ambulances, with medical equipment, patient monitoring applications and telemetry devices that ensure excellent pre-hospital management. 5G can facilitate real-time control of medical robots, enabling precise and safe interventions in performing complex procedures. 5G enables faster and more efficient data transfer, facilitating clinical trials and drug development, as these require the collection of large amounts of data from multiple sources. 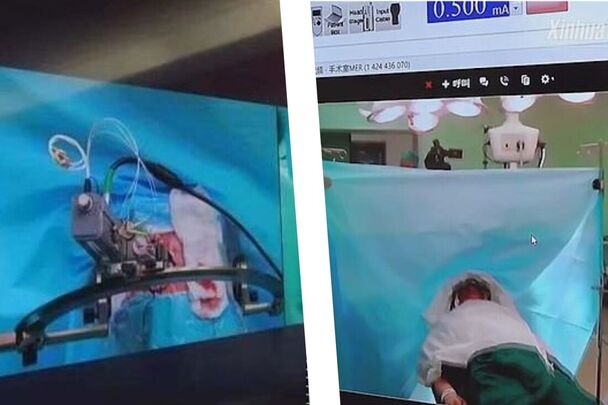 World’s first remote brain surgery using 5G | Original Images: New China TV Author: Dr. Paul ZilbermanMedical Doctor, Anaesthetist, Hadassah Medical Center Jerusalem, Israel This article addresses the notion of buoyancy and why drinking beer in space (the ISS usually orbits in the thermosphere), or any carbonated drink for that matter, does not produce the known tingling sensation we can feel in our noses here on Earth. So let’s first briefly consider what is buoyancy? In simple terms, whenever an object is put into a fluid there are several forces that act upon it. The liquid exerts a force from the bottom upwards that tries to push that object up. Then there is the liquid force itself, let’s call it weight, that pushes an object downwards. However, because the liquid pressure increases the deeper you go down into the fluid, there will always be an upwards force bigger than the downward force. This can be explained by looking at the formula for hydrostatic pressure: Hydrostatic pressure = pgh In this formula, p is the density of the liquid, g is the gravitational force (9.81 m/s2) and h is the height of the fluid column measured from the surface. Keeping all the other parameters of the formula constant, the "h" at the bottom of a submerged object will be higher than the one at its top. But we also have here another component: the "g". Well, there is practically no "g" in space, unless we artificially produce it. So, in this case, all the objects inserted or included into a fluid will just stay there. Of course, there are many other factors that play a role here, for example the superficial tension of the fluids etc., however, for the sake of simplicity I am considering here only the buoyancy. So, nothing happens with the CO2 bubbles inside the fluid because they are no lighter than the fluid that surrounds them, perhaps looking something like in this photo:  Image credit: NASA, Public domain This not mixing between the fluid and gases within creates a hard enough life for anyone who would like to enjoy a beer in space (hypothetically, at least as alcohol consumption is not permitted on the ISS), but let's also not forget the cabin temperature of roughly 20 degrees Celsius, which is way too high to enjoy an ice cold beer. If you want to cool it a bit forget leaving it outside too - just take a look at what the temperatures are "outside", unless of course you want to lick your beer like an ice-cream!
Author: Lucas RehnbergNHS Doctor - Anaesthetics & Intensive Care | MSc Space Physiology & Health   My name is Lucas, I am a doctor in the UK working in anaesthetics (or Anaesthesiology for any American readers) and intensive care medicine. I have had an interest in space medicine for over 10 years now, inspired by none other than Prof Thais Russomano who has mentored me over the years and still does. My Master’s dissertation (back in 2009) focused on CPR (cardiopulmonary resuscitation) methods in microgravity, with my continued research interest surrounding critical care in space. I am careful to say that I am a doctor with an interest in space medicine and physiology, as opposed to a ‘Space Doctor’ – as there are many individuals out there who have committed many more years than I have to this field and are vastly more experienced than I am! A club I aspire to join one day. The idea of this blog, or series of blogs, is to look at some of the latest research in space physiology and space medicine, then consider how this will play out clinically. With a particular focus on critical care and potentially worst-case scenarios when in space (or microgravity environment). Something all doctors will have done in their careers; we are equipped with the skills to critically appraise papers and then ask if they are clinically relevant, or how will it change current practice. Over the last 60 (ish) years of human space flight, there is lots of evidence to show that there are many risks when the human body has prolonged exposure to microgravity, which can affect most body systems – eyes, brain, neuro-vestibular, psychological, heart, muscle, bone, kidneys, immune system, vasculature, clotting and even some that we haven’t fully figured out yet. But then what needs to be done is to tease out how clinically relevant are these from the research, how could that potentially play out if you were the doctor in space, then how to mitigate that risk and potentially treat it.  Author: Tobias Leach3rd Year Medical Student | University of Bristol | Passionate about space!  Space provides boundless opportunities for human existence and innumerable threats to human health. The question is, are we yet prepared to deal with a catastrophic event, such as a cardiac arrest in space? Abstract
Introduction To gain an understanding of the current state of CPR in microgravity with a focus on chest compressions in the event of a sudden cardiac arrest onboard. Methods An Ovid Medline search was conducted: 17 articles were found; 12 were excluded; six additional articles were found in the references of the remaining five articles, bringing the total number of articles included to 11. These were then critically analysed. Results No CPR method currently reaches the European Resuscitation Council (ERC) guidelines. The Handstand (HS) method appears to be the strongest. Evetts-Russomano (ER) is the second strongest method. Automatic chest compression device (ACCD) performed consistently well. Conclusion CPR appears to be far more difficult in microgravity. Inconsistencies in research methodology do not help. The ER method should be used as a first contact method and the HS method should be used once the casualty is restrained. An ACCD should be considered as part of the medical equipment. Further research is needed, directly comparing all positions under the same conditions. Author: Prof. K. GanapathyHon Distinguished Professor The Tamilnadu Dr MGR Medical University; Emeritus Professor, National Academy of Medical Sciences; Past President, Telemedicine Society of India & Neurological Society of India; Director Apollo Telemedicine Networking Foundation & Apollo Tele Health Services, India ABSTRACT: Introduction: Metaverse is the augmented virtual world formed by convergence of virtual and physical space. Users interact within this created world, meeting each other virtually, immersing themselves in performing virtual activities, which subsequently could lead to real experiences. Conventionally, the healthcare “industry” is conservative in deploying future ready technology. Aims and Objectives: This overview discusses the untapped potential of metaverse applications in healthcare from a clinician’s perspective. Bereft of technical jargon, the article points out the advantages, disadvantages, limitations, and challenges in actual deployment of the metaverse in clinical practice in the real world. The exponential transformation occurring in this area is highlighted. The highly technical literature is simplified for easier comprehension. Findings: Clinical applications, use of the metaverse in training, education, and augmenting telehealth consultations, in an immersive milieu, is discussed. Direct “in-person” interaction with digital products and solutions will be a new experience for a healthcare provider and the beneficiary. The role of digital twins is illustrated. Consultation process and various clinical applications in the metaverse are outlined. Technology‑enabled futuristic training and education is discussed. Conclusion: Demonstrating significant improvement in healthcare outcomes using the metaverse will be difficult to prove. This alone will ultimately lead to the development of a business model, insurance reimbursement and behavioral modification necessary for accepting and using, a hitherto unused method in patient care. Keywords: Augmented reality and healthcare, blockchain and healthcare, metaverse and healthcare, virtual reality and healthcare 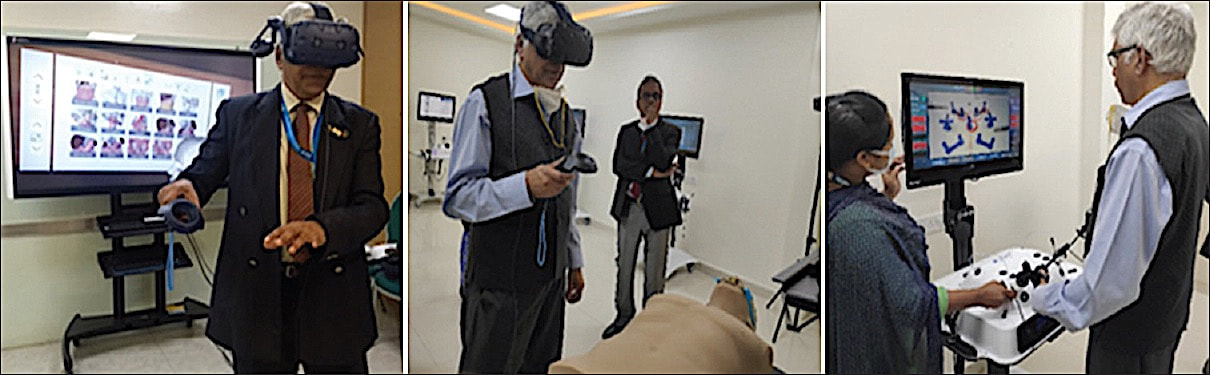 Images courtesy of Dr K Ganapathy The full article can be read and freely downloaded following this LINK
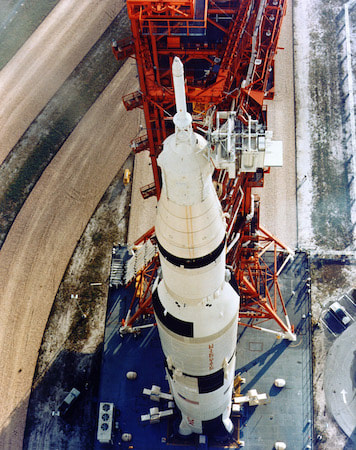
Author: Paul Zilberman MDAnaesthesiologist, Israel MOTTO: I was born in 1960. As a child I was thrilled to witness the first man in space, as per stories, in those years a direct TV transmission was still a dream. And even if it had been possible, I was one year of age, so… But later on, I was able to see the launch of the Apollo missions and the common US-Soviet programs Soyuz- Apollo. As many other terrestrials I was thrilled to watch, both from distance and close up, those “white pencils” with the painting of “The United States of America” climbing faster and faster, leaving behind a huge ball of fire… Then the first carrying rocket segment detaching and falling back to Earth… I was amazed seeing how only after a short time those “people out there” were floating and smiling, waving their hands and telling us everything is ok. I was reading about the many experiments that were carried out during the flights, I was even able to look now and then at the flight path, little understanding what were the sinusoidal lines appearing on the huge Command Center screen, where so many people were sitting in front of the computers with the microphones and earpieces connected. I didn’t understand then, exactly, why so many people were dealing with so few in space.
Well, time went on, Skylab appeared, then the ISS, the shuttles…wow…all in a lifetime. As time went on and understanding grew, on top of my medical school and, later on, anaesthesia residency, other questions arose: how do the astronauts eat, drink, wash, use the toilets? And many other daily mundane things we take for granted down here. |
Welcometo the InnovaSpace Knowledge Station Categories
All
|





 RSS Feed